

For generations of pharmacists, the drug-development pipeline has been taught as a fairly predictable sequence. A potential therapy is discovered, tested in animals, advanced into human clinical trials, reviewed by the FDA, and eventually reaches patients if the evidence supports approval.
That framework is still useful, but the science underneath it is becoming much more sophisticated.
On September 21, the FDA issued a direct final rule updating the terminology used in its regulations for nonclinical testing of drugs and biological products. The change formally recognizes that appropriate safety evidence can come not only from traditional animal studies, but also from newer approaches using human cells, organs-on-chips, computer models, and other advanced technologies. (fda.gov)
The rule does not eliminate animal testing. It does not lower the FDA’s safety standards. It does not tell drug developers that one particular technology must replace traditional studies.
What it does is remove regulatory language that could imply animal testing is the only acceptable pathway for generating certain nonclinical safety information. The FDA is replacing terms such as “animal tests” and “animal studies” with broader terms including “nonclinical tests” and “nonclinical studies,” reflecting changes Congress made through the Food and Drug Omnibus Reform Act of 2022. (fda.gov)
That may sound like a technical terminology update.
It is much more interesting than that.
The regulatory framework around drug development is beginning to formally accommodate a wider range of tools for answering one of medicine’s oldest questions:
What can we learn about a potential therapy before exposing people to it?
Drug development is becoming less dependent on one type of evidence
Animal studies have played an enormously important role in drug development. They have helped researchers evaluate toxicity, understand pharmacology, estimate exposure, and identify risks before medications reach human trials.
But animal biology is not human biology.
A model can reproduce some aspects of human physiology extremely well and others poorly. Certain toxicities may appear differently across species. Some therapeutic effects observed in animals fail to translate into humans.
That creates a fundamental scientific challenge. Researchers are trying to predict what a drug will do in a human being before enough humans have received it to know the answer directly.
New Approach Methodologies, usually shortened to NAMs, are an expanding set of tools designed to give researchers additional ways to answer that question.
FDA defines NAMs broadly. They can include human-based in vitro systems, computational modeling, and other innovative platforms used to evaluate areas such as toxicity, immunogenicity, pharmacodynamics, safety, efficacy, and product quality. The goal is not simply to replace animals for ethical reasons. The larger scientific goal is to develop methods that may sometimes provide information that is more directly relevant to human biology. (fda.gov)
Imagine, for example, creating a miniature model of human tissue that behaves in important ways like the corresponding organ.
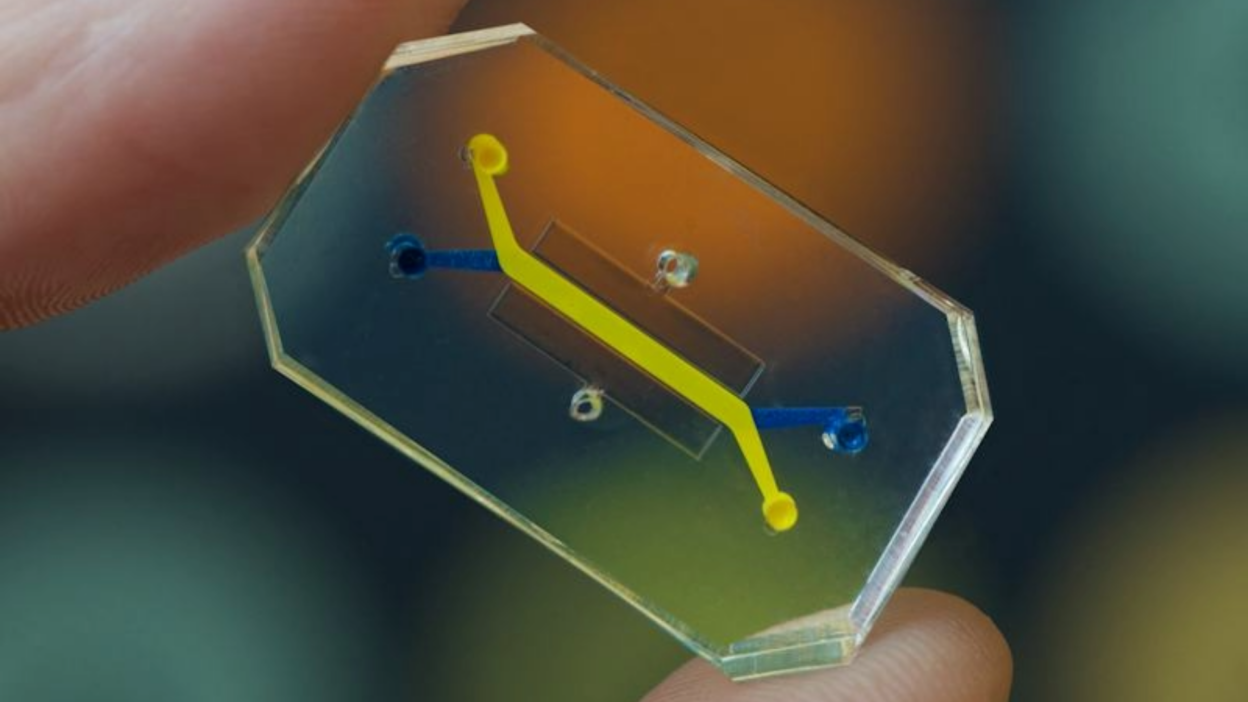
An organ-on-chip system can use living human cells arranged within a small engineered environment that attempts to reproduce aspects of how an organ functions. Depending on the design, researchers may be able to expose that system to a drug and study biological responses in a human-derived model.
Other approaches use human cells in less complex in vitro systems. Computational methods can model biological processes, predict chemical properties, or simulate aspects of drug behavior. FDA’s broader NAM work also includes areas such as in silico modeling and AI-enabled approaches. (fda.gov)
None of these methods automatically provides the answer.
That is exactly why validation is so important.
A sophisticated computer model is not useful in regulatory decision-making merely because it is technologically impressive. Researchers and regulators need to understand what the model measures, how reliably it measures it, where it performs well, where it fails, and whether it is appropriate for the specific scientific question being asked.
FDA’s March 2026 draft guidance on NAMs focuses heavily on that point. It outlines a framework for validating these methods when developers want to use NAM-generated data in drug-development submissions. (fda.gov)
The future, therefore, is unlikely to be as simple as replacing an animal with a chip.
It is more likely to involve assembling the strongest combination of evidence for the question at hand.
The preclinical pipeline is becoming an evidence ecosystem
This is what makes the September 21 rule particularly interesting.
The traditional picture of drug development can make the process look almost like a relay race: discovery hands the drug to animal testing, animal testing hands it to clinical development, and clinical development eventually hands it to regulators.
Modern drug development increasingly looks more interconnected.
A development team might combine human-cell data with computational modeling. It might incorporate pharmacology studies, molecular data, traditional animal studies where they remain useful, model-informed drug-development techniques, and eventually clinical evidence.
The question becomes less about completing a predetermined sequence of experiments and more about determining which combination of evidence most credibly answers the scientific and safety question.
FDA itself emphasizes this flexibility. The agency says its goal is not to replace one rigid testing approach with another. Animal studies can still be appropriate, while validated alternatives can be used when they provide the evidence needed to protect patients. (fda.gov)
That is an important distinction.
Scientific modernization does not mean lowering the threshold for evidence.
Ideally, it means improving the tools used to generate that evidence.
And we can already see examples of this happening.
Alongside the new rule, FDA launched a public database containing examples of NAMs found in review materials for previously approved drugs. The initial release included 25 examples. FDA cautions that these examples are illustrative, not blanket endorsements of a method for every future application. Whether a NAM is acceptable depends on its specific use, endpoint, product, data package, and regulatory context. (fda.gov)
Among the applications listed are reviews involving drugs such as remdesivir, lenacapavir, Cobenfy, momelotinib, and iptacopan, where specific non-animal methodologies appeared within the regulatory evidence package. (fda.gov)
That is useful because it moves this conversation beyond theory.
NAMs are not simply a futuristic research concept waiting for the 2030s. Some non-animal methods have already appeared in actual FDA drug-review packages.
This connects directly to the AI story pharmacists are already watching
Last week, Pharmacy Unlocked covered Novo Nordisk’s collaboration with Anthropic and the growing use of AI deeper inside pharmaceutical R&D.
That story was about technology moving upstream into the creation of medicine itself.
This FDA development represents the next layer.
The tools used to generate scientific evidence are changing, and the regulatory system is also beginning to adapt to those tools.
That combination matters.
Scientific innovation can move quickly, but drug development operates within a regulatory environment where evidence has to meet defined standards. A promising technology has limited impact if researchers do not understand how to validate it or regulators cannot confidently interpret the results.
That is why the convergence of AI, computational pharmacology, human-cell systems, organ-on-chip technology, and regulatory science is so interesting.
The future development team may not ask only, “What did the animal study show?”
It may need to understand what a computational model predicts, what a human-derived cell system demonstrates, what a microphysiological model suggests about toxicity, how those findings compare with conventional laboratory evidence, and whether the complete evidence package is strong enough to justify moving forward.
FDA’s broader modernization efforts already reflect this direction. The agency has been developing guidance around NAM validation, model-informed drug development, streamlined nonclinical programs, and the use of computational tools across drug development. (fda.gov)
That changes the knowledge base needed across pharmaceutical R&D.
Pharmacists should care because the way evidence is generated is changing
Most pharmacists will never build an organ-on-chip.
They probably do not need to.
Biomedical engineers, toxicologists, computational scientists, cell biologists, pharmacometricians, and other specialists bring deep technical expertise to these areas.
The opportunity for pharmacists is different.
PharmD training sits unusually close to the intersection between drug science and human use.
Pharmacists learn pharmacology, toxicology, pharmacokinetics, clinical evidence, medication safety, dose-response relationships, and how information generated during drug development eventually translates into decisions about real patients.
As the evidence-generation process becomes more technologically complex, people who can understand how that evidence connects to medication decisions become increasingly useful.
Consider regulatory science.
A regulatory professional working with a NAM does not only need to know that a model exists. The team needs to understand what question it answers, how it was validated, what its limitations are, and how the result fits into the broader evidence package submitted to regulators.
Consider translational medicine.
The entire purpose of translational science is to bridge discoveries made in laboratories and models with what ultimately happens in human biology. More sophisticated human-relevant models create new opportunities, but they also create new questions about how well those models predict clinical behavior.
Consider clinical pharmacology.
Computational approaches are already used to integrate pharmacokinetic, pharmacodynamic, and other information to guide dose selection and development decisions. FDA’s Model-Informed Drug Development program specifically supports quantitative modeling approaches that can improve trial efficiency and optimize dosing. (fda.gov)
Then there is toxicology, computational pharmacology, model validation, clinical development, and drug-development technology.
Not every role in those fields is suited to a PharmD. Many require specialized research or quantitative training.
But pharmacists interested in industry should understand that pharmaceutical careers are expanding well beyond the familiar categories of medical affairs, regulatory affairs, and traditional clinical development.
There is an entire scientific infrastructure surrounding how drugs get from an idea to a human trial.
That infrastructure is changing rapidly.
The most important skill may be understanding what makes evidence trustworthy
There is a broader career lesson here that extends beyond NAMs.
As science becomes more computational and more AI-enabled, generating an answer may become easier.
Determining whether the answer should be trusted becomes more valuable.
A computer model can produce a prediction.
A human-cell assay can produce a result.
An organ-on-chip system can reproduce aspects of tissue behavior.
An AI model can identify a pattern.
But somebody still has to determine what that result means.
Was the method validated for this use?
Does the model reproduce the biological mechanism that matters?
Is the endpoint relevant to the human risk being evaluated?
Could another explanation produce the same result?
How does this evidence compare with other studies?
What uncertainty remains?
Is the evidence strong enough to move a drug into humans?
Does additional testing still need to happen?
Those are scientific judgment questions.
Pharmacists are already trained to think this way when evaluating clinical literature. We ask whether a trial population matches the patient in front of us, whether the endpoint is clinically meaningful, whether a result is statistically significant but practically irrelevant, and whether limitations change how confidently we should apply the evidence.
The context is different in preclinical science, but the intellectual discipline is similar.
How was this evidence generated, how reliable is it, and what decision should it support?
That mindset will become increasingly useful as the tools generating the evidence change.
The transition will be gradual, not overnight
There is a temptation with announcements like this to describe an immediate replacement of animal testing.
That is not what happened.
FDA explicitly says the new rule does not prohibit animal studies, does not impose a particular testing approach, and does not change the agency’s evidentiary standards. Developers may use NAMs when the methods are adequately validated and appropriate for the product and regulatory question. (fda.gov)
The rule itself is also being issued through the direct final rule process. FDA simultaneously published a companion proposed rule. If the agency receives significant adverse comments on the direct final rule, it can withdraw it and continue through the standard notice-and-comment process. (fda.gov)
So this is not a moment where the old drug-development pipeline disappears.
It is another step in a longer transition.
FDA has been building toward this through guidance, research programs, public workshops, qualification pathways, and earlier efforts to reduce or refine animal testing. The agency’s NAM resource center now brings many of those initiatives into one place. (fda.gov)
The direction is becoming clearer.
The regulator is making room for more human-relevant and computational approaches when the science supports them.
This week, learn one term: New Approach Methodologies
For pharmacists interested in pharmaceutical industry, regulatory science, research, or simply understanding where drug development is heading, the practical action this week is simple.
Learn what New Approach Methodologies means.
Then go one step further.
FDA’s new public database lets you look at specific examples where NAMs have already appeared in approved-drug review materials. Choose one.
You might look at an in vitro sensitization assay used in a drug-development package or another non-animal method included in an FDA review. Do not worry about mastering the entire technology.
Ask three questions instead.
What problem was the method trying to answer?
Why could this approach provide useful evidence?
What would regulators need to know before trusting that result?
That exercise will teach you something much more valuable than memorizing another acronym.
It will help you understand how an emerging scientific method becomes regulatory evidence.
That is the part pharmacists interested in the future of drug development should watch.
Because the next generation of medicines may be developed using an evidence ecosystem that looks very different from the one many of us learned about in pharmacy school.
Human cells may contribute more information.
Organs-on-chips may answer questions that were difficult to model previously.
Computational systems may allow researchers to test hypotheses before running expensive experiments.
AI may help scientists build or interpret those models.
Traditional laboratory and animal evidence may still remain important when appropriate.
And eventually, all of that information has to be translated into one fundamental decision:
Is there enough credible evidence to responsibly move this medicine closer to a patient?
That is where the future of drug development becomes especially relevant to pharmacy.
The technology is changing.
The standard remains evidence.
And pharmacists who understand how new forms of evidence are generated, validated, and translated into medication decisions will have another way to participate in what comes next.
Resources & Citations
1. U.S. Food and Drug Administration. “FDA Updates Regulations to Advance Innovative Alternatives to Animal Testing.” September 21, 2026.
Primary FDA announcement describing the direct final rule, its recognition of non-animal methods including human-cell systems, organs-on-chips and computer models, the terminology changes to “nonclinical tests” and “nonclinical studies,” maintenance of existing evidentiary standards, and the accompanying NAM use-case database. (fda.gov)
FDA September 21 rule announcement
2. U.S. Food and Drug Administration. “New Approach Methodologies (NAMs).” Updated September 2026.
FDA’s central resource describing NAMs, their definition, regulatory activities, relevant guidance, streamlined nonclinical approaches, organ-on-chip and computational technologies, and the broader agency strategy for reducing, replacing, or refining animal testing when scientifically appropriate. (fda.gov)
FDA New Approach Methodologies resource center
3. U.S. Food and Drug Administration. “New Approach Methodologies (NAMs) Database of Use Case Examples.” September 2026.
FDA database of selected examples from publicly available review materials showing how specific NAMs have appeared in approved-drug applications. FDA emphasizes that these examples are illustrative and do not guarantee that the same method will be accepted for another product or regulatory question. (fda.gov)
FDA NAM use-case database
4. U.S. Food and Drug Administration. “General Considerations for the Use of New Approach Methodologies in Drug Development.” Draft Guidance for Industry. March 2026.
FDA draft guidance providing a validation framework and general scientific recommendations for drug developers seeking to use NAM-generated data in regulatory submissions. The guidance emphasizes study design, reporting, context of use, and establishing confidence that a method is fit for its intended purpose. (fda.gov)
FDA draft NAM guidance
5. U.S. Food and Drug Administration. “FDA Actions to Accelerate and Modernize Early and Late-Stage Clinical Development.” September 2026.
FDA overview of current drug-development modernization efforts, including New Approach Methodologies, quantitative systems pharmacology, streamlined nonclinical programs, and other initiatives intended to modernize how evidence is generated across development. (fda.gov)
FDA clinical-development modernization overview
6. U.S. Food and Drug Administration, Office of Clinical Pharmacology. “Model-Informed Drug Development Paired Meeting Program.” 2026.
FDA resource describing the use of quantitative modeling methods integrating preclinical and clinical information to improve clinical-trial efficiency, support risk-benefit evaluation, and optimize dosing. (fda.gov)
FDA Office of Clinical Pharmacology